Saturday, September 24, 2011

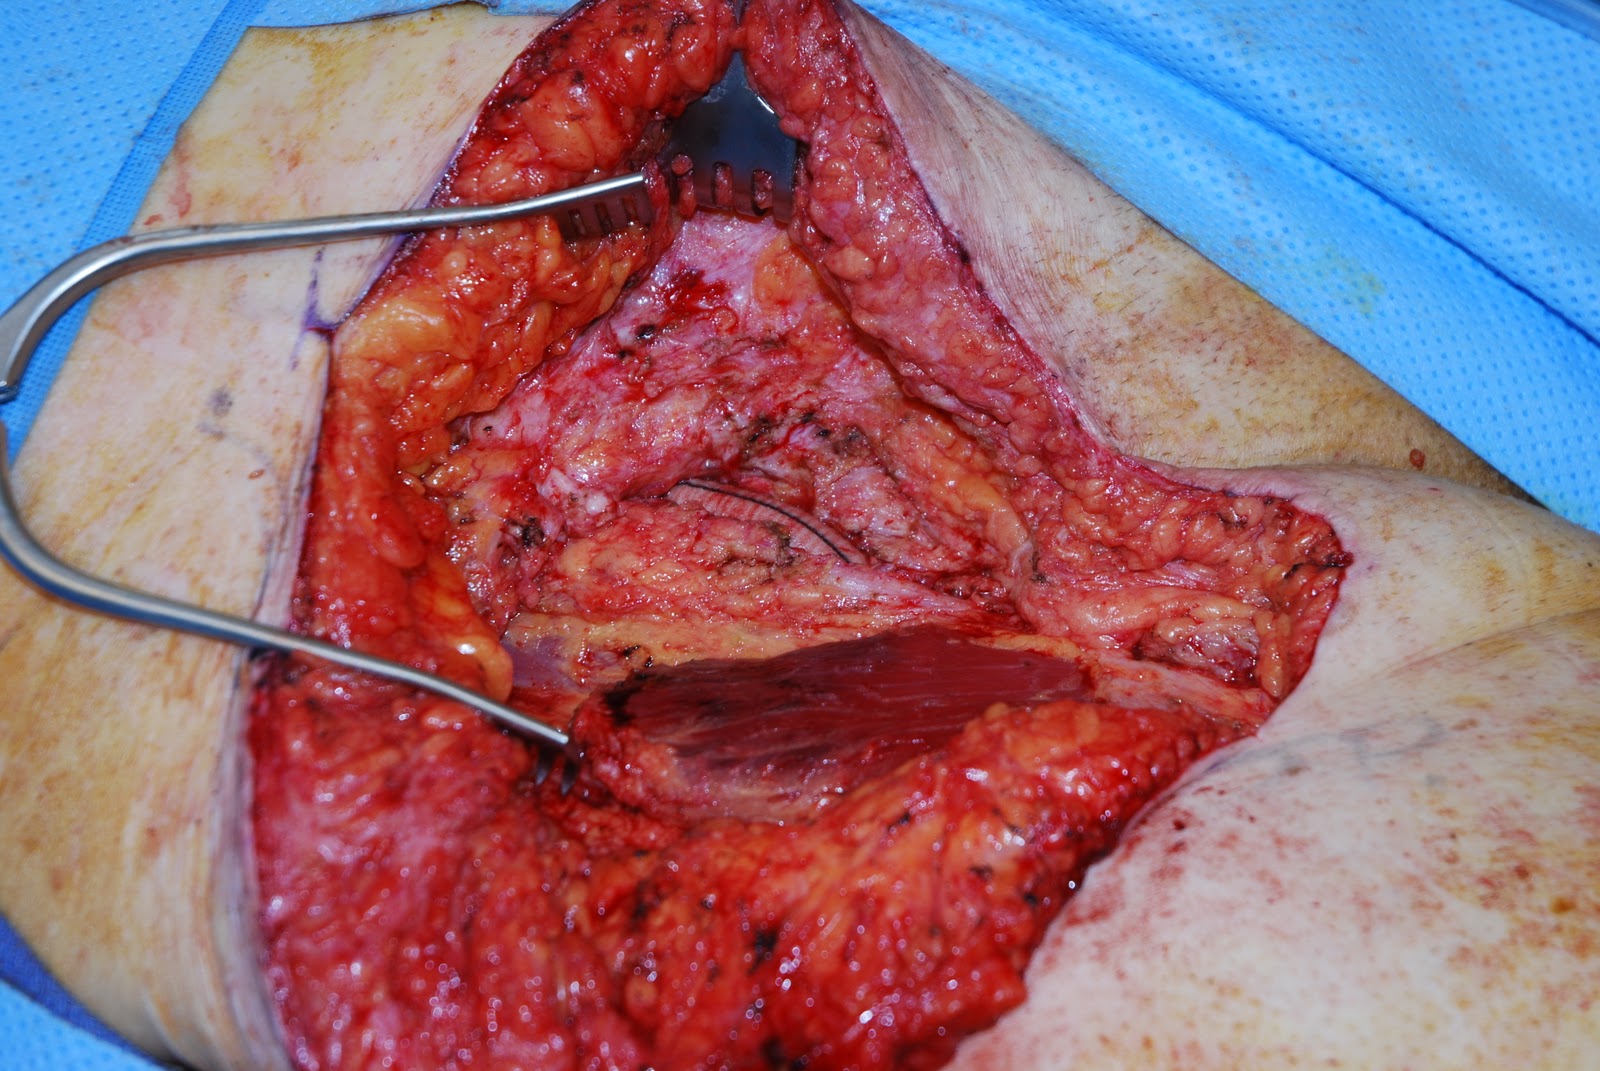
Latisimus Flap for Closure of Complex Posterior Trunk Radiation Wounds


Radiation is often a necessary adjuvant in the treatment of many cancers. While radiation is often necessary in cancer therapy, the radiation can also cause damage to normal healthy tissue and prevent wound healing.
Closure of the radiated wound is often one of the most challenging problems the Plastic & Reconstructive Surgeon can face. The key to closing radiated wounds is adequate debridement. Often adequate debridement can create a much larger wound that the original and often much larger than anticipated by both patient and surgeon.


After adequate debridement has been performed, the next important step in reconstruction is to make sure that healthy tissue is brought into the area affected to allow wound closure. In some cases, tissue from an adjacent area of the body can be used, occasionally regional tissue may be used, and in some cases distant tissue is used to be brought into the area to allow wound closure. When tissue from a remote area of the body is used, this is called free tissue transfer or microsurgical anastomosis.


In this case a large posterior trunk wound was present after successful cancer removal and successful radiation therapy. The wound was thoroughly debrided to relatively healthy tissue. A wound VAC was then placed on the posterior trunk to promote blood perfusion and as a bridge to determine the final wound size and plan reconstruction.
In this case, a latisimus myocutaneous flap was used to bring both muscle to cover exposed bone and skin to fill a defect. A small skin graft was placed on the latisimus muscle to prevent too tight of a wound closure. The skin graft however contracts over time and can often eventually be excised and the wound closed with one skin paddle.

Monday, May 2, 2011

Lower Extremity Flap Surgery. Journal of Reconstructive Microsurgery Publication

I am very fortunate to publish in the Journal of Reconstructive Microsurgery with Dr. Neil Jones on lower extremity reconstruction.

Saturday, April 9, 2011

Stacked DIEP Flap. EJ Turndown and SIEV Extension Graft


Occasionally in breast reconstruction a large portion of the abdominal flap needs to be delivered to the chest either to have significant skin surface area to replace a large defect or a large volume needs to be delivered to re-create the breast.

The stacked DIEP flap has been described to transfer a large portion of the abdominal flap to the chest wall. During my microsurgical study with Dr. Ashjian we have discovered that the venous outflow is a large determinant of flap success with stacked DIEP flaps. There is often more than sufficient arterial blood flow to sustain the volume of fat transferred when using the deep system. This is often evident when the flap is perfusing in situ on the adomen with the deep system connected and the superficial system clamped. Typically, the lateral zones develop congestion when the superficial veins are clipped. When the superficial veins are released there is often blood flow returning from the veins. If there was a lack of arterial blood flow or no connection between the deep and superficial system, then there would be no blood flow from the superficial veins.

Therefore with stacked DIEP flaps, additional venous outflow is needed to accommodate the flap volume. On the left side the venous outflow can be challenging given the traditionally smaller size of the internal mammary vein. The external jugular when mobilized and turned down into the wound can often be short depending on the body habitus of the patient. On occasion the surgeon can be presented with a patient with a short neck and long torso. This makes the reach of the EJ to the flap outflow vein challenging if the flap is already connected to the internal mammary artery. We have used the greater saphenous vein as an extension graft from the EJ to the flap. It is easier to anastomose the greater saphenous vein to the EJ extracorporeally and then pass the graft-EJ anastomosis subcutaneously into the chest.


In some situations, if the superficial epigastric veins have been preserved during flap dissection and are of adequate length, these can be used instead of the greater saphenous vein to lengthen the external jugular vein reach so that venous outflow can be augmented in the flap. This can be very helpful if both SIEVs are preserved during dissection as one can be used to anastomose to the other, offering favorable size match.


When the superficial vein is anastamosed to the external jugular vein, or other adeuate venous drainage system, with the other superficial epigastric vein as an extension graft we have found it possible to maintain almost all of the flap volume for breast reconstrution. We therefore underscore the utility of the superficial venous system in allowing venous egress of the contralateral flap and lateral flap zones.

Thursday, February 24, 2011

Zone II Flexor Tendon Injury. Repairing "No Man's Land" to Optimize Results.


Proper tendon repair to achieve maximal results with zone II flexor tendon injuries requires strict compliance of the patient with hand therapy. It is of paramount importance to adhere to post-operative care to ensure that tendons glide appropriately through the pulley system so that after the tendon heals, proper excursion can be restored to the hand to maximize outcome.

http://www.drbriandickinson.com/

Tuesday, February 8, 2011

The Sartorius Muscle Flap for Coverage of Aorto-Bifemoral Grafts

As the number of patients who are older than 65 years of age continues to gow in the United States, we are beging to see fatigue of implantable devices that may need to be replaced, exchanged, or upgraded. As  a person ages, so do the vessels in the body that supply blood and oxygen to the organs. Diseases of the blood vessels that causes narrowing or weakening of the vessel wall include is called perihperal vascular disease.

The prevalence of peripheral vascular disease in the general population is 12–14%, affecting up to 20% of those over 70. Peripheral vascular disease affects 1 in 3 diabetics over the age of 50.
In the USA peripheral arterial disease affects 12–20 percent of Americans age 65 and older. Approximately 10 million Americans have PVD.
Surgical treatment of peripheral vascular disease includes stenting open arteries that are narrowed or often replacing segements of arteries with grafts. Ocassionally, these grafts can become infected or exposed and necessate the coordinated efforts of Plastic & Reonstructive Surgeons with Vascular Surgeons to maximize outcomes.
 
The sartorius muscle flap is a type IV muscle with a segmental blood supply. The muscle is often used in the setting of exposed, infected, or replaced bypass grafts to provided soft tissue coverage to close an anatomic "dead space' or help deliver antibiotics to the area.
 
The photo series below depicts a femoral limb of an aorto-bifemoral graft which has been covered with a sartorius flap to help deliver antibiotics to the region so that the graft deliver blood to perfused the leg.


http://www.drbriandickinson.com/

Thursday, January 6, 2011

Limb Salvage with Free Rectus Muscle Flap

Occlusion of vessels of the leg can significantly impair wound healing when the integrity of the skin is violated. In the distal third of the leg where there is limited leg laxity, it is necessary to bring well vascularized tissue from one region of the body to another.


When one of the three blood vessels to the leg is occluded, it is important to maintain the remaining blood supply of the lower extremity. In that case, the rectus muscle is removed from the abdomen and transferred to the leg using and end-to-side anastamosis off of the posterior tibial vessel. Using an end-to-side anastamosis can preserve the blood supply to the foot.


Drains are placed beneath the muscle and the muscle is then covered with a split thickness skin graft. Elevation of the lower extremity is important post-operatively.

http://www.drbriandickinson.com/

Saturday, December 25, 2010

Axillary Flap for Closure of Chest Wall Defects


Long standing burn scars can have tumors arise in them called Marjolin's Ulcers. It is important to excise these ulcers with wide surgical margins.


Often the resulting defect that occurs can not be closed primarily and tissue needs to be borrowed from one region of the body and transferred into the defect. The axillary flap can be easily rotated into close defects on the anterior chest.

This flap allows for a better contour of the chest wall skin withou a visible or palpable depression that may occur with a skin graft.


Once the anterior chest wall wound is closed, drains are placed to evacuate any fluid from beneath the wound to prevent infection.


Post-operatively, the flap allows for adequate contour of the chest and for a closed wound.

It is not uncommon for many patients to have a wound or lesion present on their body for quite sometime. Often as these lesions are wounds grow larger, it becomes more difficult to excise, clean, or close these wounds.

What it is important for patients to know, is that there is always a solution or help that they can receive from Plastic & Reconstructive surgeons to make the wound cleaner, more manageable, or possibly close with a flap.

While the reconstructive process can often take time, patients are always happier with a closed wound that they no longer need to take care of.

http://www.drbriandickinson.com/